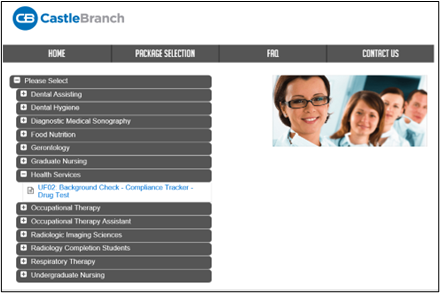
Please use the link below to order your DISA Healthcare (formerly CastleBranch) profile and select the correct package code.
To place your order:
https://portal.castlebranch.com/UE96
Steps:
Click “Place Order.”
Open the “Please Select” dropdown menu.
Choose Health Services.
Select the UF02 package code (for HA or CPH). Select UX09 for Health Informatics.
Follow the on-screen instructions to complete your order.
UF02/UX09 Package Includes:
Background check, drug test, and Medical Document Manager.
Drug testing is completed through LabCorp (925 S. Green River Rd., Evansville, IN), and the cost is included in the package.
The email address you provide will become your username.
Contact DISA Healthcare (formerly CastleBranch): 888.723.4263 or customerservice@disahealthcare.com
Download, complete, and reupload the Social Media & Digital Content Policy form.
The form is available within this requirement.
One of the following is required:
2 vaccinations OR
Positive antibody titer for (lab report OR physician verification of titer results required) for all 3 components.
If your series is in process, submit where you are in the series, and new alerts will be created for you to complete the series.
If your titer is negative or equivocal, new alerts will be created for you to repeat the series.
One of the following is required:
2 vaccinations OR
Positive antibody titer (lab report OR physician verification of titer results required) OR
Medically documented history of the disease that has been verified by a physician or nurse practitioner and contains their signature.
If your series is in process, submit where you are in the series, and new alerts will be created for you to complete the series.
If your titer was negative or equivocal, new alerts will be created for you to repeat the series.
One of the following is required:
3 vaccinations AND a positive antibody titer (lab report OR physician verification of results required) OR
Documentation of 2 Heplisav-B vaccinations AND a positive antibody titer (lab report OR physician verification of results required) OR
Positive antibody titer (lab report OR physician verification of results required)
If your series is in process, submit where you are and new alerts will be created for you to complete the series and titer (performed within 2 months of completing series).
If your titer is negative or equivocal, new alerts will be created for you to submit documentation of a repeat series (administered after your titer) and a follow up titer (lab report OR physician verification of results required) performed within 2 months of completing repeat series.
If your repeat titer is also negative or equivocal, you will be considered a non-responder and must upload your titer ALONG WITH the non-responder form (available to download from this requirement.
One of the following is required:
2 step TB skin test (2 separate TB Skin Tests within 1-3 weeks apart) within the past 12 months OR
QuantiFERON Gold blood test within the past 6 months (negative laboratory report OR physician verification of negative results required) OR
T-Spot TB blood test within the past 6 months (negative laboratory report or physician verification of negative results required) OR
If positive results, provide a clear Chest X-Ray dated anytime after the positive result (lab report OR physician verification of results required)
Renewal will be set for 1 year for skin test, x-rays, and questionnaire submissions. Renewal will be set for 6 months for blood test submissions.
Upon renewal, one of the following is required:
If attending a facility that does NOT require annual testing, print your TB score from the annual education module and upload the document to this requirement.
No renewal required OR, if attending education at a facility that requires annual testing, submit one of the following:
1-step TB skin test OR
QuantiFERON Gold blood test within the past 6 months (negative laboratory report or physician verification of negative results required) OR
T-Spot TB blood test within the past 6 months (negative laboratory report or physician verification of negative results required) OR, if you provided a chest x-ray for your initial requirement, a TB questionnaire is required.
Documentation of a Td or Tdap booster within the past 10 years.
The renewal date will be set for 10 years from the administered date of the booster.
One of the following is required:
Documentation of a flu vaccination administered before 12/1 of the current flu season (Documentation does NOT need to indicate that the vaccination you received is from a batch for the current flu season.) OR
Declination of flu vaccine for medical reasons along with statement from Healthcare provider verifying medical allergy.
The renewal date will be set for 10/10 of the following flu season.
Upon renewal one of the following is required:
Documentation of a flu vaccine administered between 08/01 and 10/10 of the current flu season, OR
Declination of flu vaccine for medical reasons along with statement from Healthcare provider verifying medical allergy.
One of the following is required:
American Heart Association BLS for Healthcare Providers (Instructor Led Training) OR
American Red Cross BLS/CPR for Healthcare Providers
You should submit proof of an approved American Heart Association or American Red Cross card, e-card, or certification of completion.
Renewal date will be based on the expiration date.
One of the following is required:
Download print and complete the one-page Report of Physical Examination and upload to this requirement OR
Download print and complete the medical evaluation attestation form and upload to this requirement.
Documentation MUST be signed by a medical professional.
Download, print & complete the 2-page Report of Medical History form and upload to this requirement.
Go to the KCNHP website: https://www.usi.edu/health/faculty-staff-resources/hipaa-module
Print your HIPAA score and upload the document to this requirement.
Renewal will be set for 1 year.
Download, print, complete, and submit the attached Confidentiality Statement form to fulfill this requirement.
Upload your signed Workforce Member Review of HIPAA policies and procedures document to fulfill this requirement.
Renewal will be set for 09/01 each year.
Note to students: Form can be found on KCNHP website. (https://www.usi.edu/health/faculty-staff-resources/hipaa-module)
Print your OSHA score out and upload the document to this requirement. (https://www.usi.edu/health/faculty-staff-resources/hipaa-module)
Download, print, complete and re-submit the CNHP Lab and Clinical Waiver form to this requirement.
Renewal will be set for 1 year.
Submit documentation of a 10-panel (minimum) drug screen completed within the past 3 months, including the lab report.
· If results are negative: You will be cleared for placement in your program.
· If results are positive: You must provide documentation from your physician confirming a valid prescription for the substance(s) identified.
· If positive results are submitted without appropriate physician documentation, the requirement will be rejected, and you will need to contact your program administrator.